
Month End Sale Special - 75% Discount Offer - Ends in 0d 00h 00m 00s - Coupon code: big75certs

Free and Premium ACDIS CCDS Dumps Questions Answers

Page: 1 / 11
Total 150 questions

Certified Clinical Documentation Specialist Questions and Answers

Question 1

A pregnant patient is admitted at 30 weeks' gestation with acute pyelonephritis complicating pregnancy. Which general sequencing principle applies?

Options:

A.

Pyelonephritis is always sequenced before any obstetric code

B.

The appropriate Chapter 15 pregnancy complication code generally receives sequencing priority

C.

Pregnancy is ignored because the infection is unrelated to delivery

D.

A symptom code must be principal diagnosis

Buy Now
Question 2

When reviewing a patient's chart in the ICU, a CDI specialist determines a query needs to be placed. As the query is being written, the attending physician is leaving the patient's room after completing rounds. Which of the following is the BEST action to take?

Options:

A.

Wait to see what the physician documents

B.

Complete the written query and submit to the physician

C.

Review another chart

D.

Query the physician verbally

Question 3

A physician is completing rounds when a CDI specialist identifies conflicting documentation that can be clarified immediately. Which approach is MOST appropriate?

Options:

A.

Avoid verbal discussion because all queries must be electronic

B.

Discuss the issue professionally with the physician and ensure the clarification process meets organizational query documentation requirements

C.

Tell the physician which diagnosis produces the correct MS-DRG

D.

Wait until final billing because concurrent clarification is inappropriate

Question 4

A patient underwent open small bowel resection with anastomosis for colon cancer. The physician notes, "Post-op ileus, awaiting return of bowel function." Which of the following actions should a CDI specialist take FIRST?

Options:

A.

Apply a secondary diagnosis code for postoperative ileus

B.

Assign a complication code along with the code for postoperative ileus

C.

Query if the ileus was a postoperative complication or expected outcome

D.

Discuss the matter with the physician advisor or the CDI manager

Question 5

A hospital reports 80 observed deaths when its risk-adjustment methodology predicted 100 expected deaths. What is the observed-to-expected mortality ratio, and what does it indicate?

Options:

A.

0.80; observed deaths are 20% below expected

B.

0.80; observed deaths are 80% above expected

C.

1.25; observed deaths are 25% below expected

D.

1.25; observed deaths are 25% above expected

Question 6

A patient undergoes colorectal surgery. On postoperative day 2, the physician documents “ileus.” The record shows absent bowel sounds and abdominal distention, but the surgeon also states that delayed bowel function is expected at this stage of recovery. Which action is MOST appropriate?

Options:

A.

Automatically code postoperative ileus as a surgical complication

B.

Query the provider regarding whether the ileus represents an expected postoperative condition or a complication

C.

Remove the diagnosis because postoperative ileus is never reportable

D.

Assign intestinal obstruction instead

Question 7

A patient is admitted with a stage 4 pressure ulcer of the right heel. The physician documents the pressure-ulcer diagnosis and location. The wound-care nurse documents stage 4. Which statement is MOST accurate?

Options:

A.

Stage 4 cannot be coded unless the physician documents the stage personally

B.

Qualified non-provider documentation may be used to identify the pressure-ulcer stage

C.

The nurse may establish both the pressure-ulcer diagnosis and all associated medical diagnoses

D.

Pressure-ulcer stage is irrelevant to coding

Question 8

Which of the following secondary diagnoses has the MOST positive monetary impact on MS-DRG reimbursement?

Options:

A.

Acute exacerbation of COPD

B.

Acute delirium

C.

Acute diastolic heart failure

D.

Acute kidney injury

Question 9

A hospital's case is assigned to an MS-DRG with a relative weight of 2.0000. What does the relative weight primarily indicate?

Options:

A.

The patient is twice as sick as the average Medicare patient

B.

The case is expected to consume approximately twice the average relative resources

C.

The hospital should bill twice its normal charges

D.

The patient's expected mortality is twice the national rate

Question 10

A patient was admitted with weakness, loss of appetite, hemoglobin 7.8, WBC 2,700, and platelet count 58. The admitting diagnoses on the history and physical were anemia, leukopenia, decreased platelets, and rule out myelodysplastic syndrome. Based on these clinical indicators a CDI specialist should query for which of the following conditions?

Options:

A.

thrombocytopenia

B.

myelophthisis

C.

pancytopenia

D.

aplastic anemia

Question 11

Under the Inpatient Prospective Payment System, the PACT rule affects MS-DRG payment. PACT is an acronym for which of the following?

Options:

A.

Post-Acute Care Transition

B.

Post-Admission Compliance Transfer

C.

Pre-Admission Care Transition

D.

Post-Acute Care Transfer

Question 12

A patient has chronic gastroesophageal reflux disease listed in the past medical history. During the current hospitalization for bacterial pneumonia, GERD receives no clinical evaluation, treatment, diagnostic testing, increased nursing monitoring, or effect on length of stay. Which statement is MOST accurate?

Options:

A.

GERD must be coded because it is a chronic disease

B.

GERD must be coded because it appears in the medical record

C.

GERD generally does not meet the criteria for a reportable secondary diagnosis

D.

GERD should be coded only if it is a CC

Question 13

A patient develops chest pain and elevated troponins while receiving care in the emergency department. The physician diagnoses an NSTEMI. Several hours later, an inpatient admission order is written. How should the NSTEMI generally be considered for POA purposes?

Options:

A.

Not present on admission because it occurred before the patient reached an inpatient bed

B.

Present on admission because it was present when the inpatient admission order occurred

C.

POA status cannot be assigned to a principal diagnosis

D.

Hospital acquired because the condition occurred on hospital property

Question 14

An 82-year-old patient with a urinary infection develops an acute fluctuating disturbance in attention, disorganized thinking, and altered level of consciousness. The family states the patient was cognitively normal three days earlier. Which condition is MOST consistent with this presentation?

Options:

A.

Chronic dementia

B.

Delirium

C.

Persistent vegetative state

D.

Intellectual disability

Question 15

Which of the following diagnoses is classified as a major complication/comorbidity (MCC) under the FY 2026 MS-DRG system?

Options:

A.

Uncomplicated COPD

B.

Bacteremia

C.

Chronic systolic heart failure

D.

Severe protein-calorie malnutrition

Question 16

At discharge, the physician documents, “Possible gram-negative pneumonia.” No later documentation rules out the condition. How should the diagnosis generally be handled for an inpatient admission?

Options:

A.

Code only cough and fever

B.

Code the possible pneumonia as if established

C.

Code unspecified pneumonia only

D.

Do not report pneumonia because “possible” is never reportable

Question 17

Which CMS resource contains the complete FY 2026 lists of diagnoses classified as MCCs and CCs for MS-DRG purposes?

Options:

A.

Hospital Consumer Assessment survey

B.

FY 2026 IPPS Final Rule Tables, including Tables 6I and 6J

C.

Medicare Physician Fee Schedule only

D.

National Coverage Determination manual

Question 18

The table below shows physician performance:
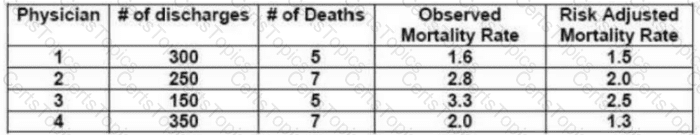
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?

Options:

A.

1

B.

2

C.

3

D.

4

Question 19

A patient's baseline creatinine is 1.1 mg/dL. On admission it is 1.2 mg/dL, and 36 hours later it rises to 2.4 mg/dL after prolonged hypotension. Urine output declines substantially. Which condition presents the strongest clarification opportunity?

Options:

A.

Chronic kidney disease

B.

Acute kidney injury

C.

End-stage renal disease

D.

Nephrotic syndrome

Question 20

A CDI program is piloting a new query form to better capture the documentation of pneumonia specificity. Which of the following would be the BEST indicator to determine the effectiveness of the query form?

Options:

A.

Increased provider response rate

B.

Increased provider agreement rate

C.

Increased volume of cases in the simple pneumonia DRGs

D.

Increased volume of cases in the respiratory infection DRGs

Question 21

A wound care nurse documents an assessment and care of a pressure ulcer. For coding purposes, the wound care nurse's documentation can be used to assign which of the following?

Options:

A.

POA status

B.

The diagnosis

C.

Location

D.

Stage

Question 22

Which pressure-ulcer category is specifically included in the traditional CMS HAC payment policy when the condition is not present on admission?

Options:

A.

Stage 1 and stage 2 pressure ulcers

B.

Stage 3 and stage 4 pressure ulcers

C.

All pressure injuries regardless of stage

D.

Healed pressure ulcers only

Question 23

A patient is admitted with a stage 3 sacral pressure ulcer. During hospitalization, the wound deteriorates and is documented as stage 4 at the same site. Which reporting approach is appropriate?

Options:

A.

Report only stage 3 because that was the POA stage

B.

Report only stage 4 because it is the highest stage

C.

Report codes representing the stage on admission and the highest stage reached during the stay

D.

Use an unstageable pressure-ulcer code

Question 24

Which statement BEST defines the principal diagnosis for an inpatient hospitalization?

Options:

A.

The diagnosis with the highest MS-DRG relative weight

B.

The first condition documented in the emergency department

C.

The condition established after study to be chiefly responsible for occasioning the hospital admission

D.

The diagnosis requiring the greatest number of medications

Question 25

A hospital's query policy states that all answered queries will be retained, but all unanswered queries that might delay billing will be permanently destroyed. What is the PRIMARY compliance concern?

Options:

A.

Providers should never receive written queries

B.

Selectively destroying unanswered queries undermines a consistent and auditable query-retention process

C.

Only answered queries are legally permitted in the health record

D.

All queries must remain in the permanent medical record forever

Question 26

A CDI specialist reviews the MS-DRG mismatch report and notes a difference in a case. The coder noted that a current Coding Clinic affects the final coding of the record, which changed the MS-DRG assignment. To BEST understand this discrepancy, the specialist should FIRST:

Options:

A.

Give the case to the coding manager

B.

Review the final codes with the identified Coding Clinic

C.

Discuss the case with the coder by phone or in person

D.

Forward the case for billing without CDI review

Question 27

A patient is admitted with shortness of breath and dyspnea. Physical examination documents percussion dullness of the chest and decreased breath sounds. A chest x-ray indicates an increase in fluid with complete opacification of the hemithorax and mediastinal shift to the contralateral side. Which of the following conditions should be queried with the physician?

Options:

A.

Bronchiectasis

B.

Congestive heart failure

C.

Pleural effusion

D.

Pneumonia

Question 28

A CDI manager is evaluating physician participation in the program. Which metric most strongly indicates poor physician engagement?

Options:

A.

Number of queries generated

B.

Number of unanswered queries

C.

Number of agreed-with queries

D.

Number of disagreed-with queries

Question 29

At discharge, the attending physician documents, “Probable aspiration pneumonia causing the patient's respiratory symptoms.” The patient is an inpatient. No subsequent documentation rules out aspiration pneumonia. How should the diagnosis be handled for inpatient coding?

Options:

A.

Code only the respiratory symptoms

B.

Code aspiration pneumonia as if established

C.

Query because “probable” diagnoses can never be coded

D.

Code unspecified pneumonia only

Question 30

A patient with severe cachexia and substantial loss of appetite requires pharmacologic treatment to stimulate appetite. Which of the following medications is most commonly associated with this indication?

Options:

A.

Sibutramine

B.

Memantine

C.

Megestrol acetate

D.

Levothyroxine

Question 31

Hospital A is developing a query policy. Open-ended queries will be encouraged. The provider is expected to document on the query form, which will be retained as part of the health record. Hospital A will remove any unanswered queries and shred them to avoid any incomplete forms within the health record. Which of the following is considered a high-risk query practice?

Options:

A.

Shredding unanswered query forms

B.

Keeping query forms as part of the health record

C.

Adding a new diagnosis as a multiple-choice option for a query

D.

Using a yes/no query format when appropriate

Question 32

A patient is admitted with TIA, right-sided weakness, and slurred speech. The physician's physical examination notes that the patient's right-sided weakness continues, but the slurred speech has resolved. A CT scan of the brain reveals a new hypodense area. The most specific diagnosis to query is acute:

Options:

A.

Encephalopathy

B.

Cerebral infarction

C.

Transient global amnesia

D.

Transient cerebral ischemia

Question 33

A patient with an indwelling central venous catheter develops fever and positive blood cultures for Staphylococcus aureus. The physician documents “bacteremia” but does not establish whether the catheter caused the infection. Which action is MOST appropriate?

Options:

A.

Automatically code a central-line infection

B.

Query the provider regarding the relationship between the catheter and infection

C.

Assume the catheter is unrelated because bacteremia was documented first

D.

Code sepsis because the blood culture is positive

Question 34

A pregnant female presents to the ED with diarrhea, cramps, nausea, and vomiting for the past 12 hours. She was admitted with enteritis due to Clostridium difficile and provided IV fluids. Which of the following coding guidelines applies to determining the principal diagnosis for this patient?

Options:

A.

sequencing related to etiology manifestation codes

B.

signs & symptoms, and ill-defined condition codes

C.

complications of pregnancy, childbirth, and puerperium codes

D.

infectious and parasitic codes

Question 35

A patient is admitted with sepsis due to an E. coli urinary tract infection. The provider also documents acute kidney injury due to the sepsis and “severe sepsis without septic shock.” Which sequencing is most appropriate?

Options:

A.

Severe sepsis code first, followed by acute kidney injury

B.

Sepsis first, followed by severe sepsis and acute kidney injury

C.

Urinary tract infection first, followed by sepsis

D.

Acute kidney injury first, followed by urinary tract infection

Question 36

A patient is admitted with alcohol intoxication. The H & P notes increased tolerance related to alcohol consumption, desire to drink despite impaired liver functions, and unsuccessful attempts to stop drinking. Identify the query opportunity related to alcohol consumption.

Options:

A.

Withdrawal

B.

Delirium tremens

C.

Dependence

D.

Abuse

Question 37

A patient presents to the ED following a motor vehicle crash with a lacerated spleen. The patient's BP is 80/60, HR is 160, and the patient receives dopamine, a 2-L saline bolus, and 3 units of PRBCs. The physician documents MVA with lacerated spleen. Based on these clinical indicators, which of the following conditions would BEST reflect the accurate acuity of this patient?

Options:

A.

Acute blood loss anemia

B.

Hypovolemic shock

C.

SIRS due to trauma

D.

Ruptured spleen

Question 38

A CDI specialist has been asked to present a report to hospital administration that will demonstrate the CDI program's impact over time. Which of the following reports will BEST accomplish this?

Options:

A.

document showing each CDI specialist's query rate

B.

pie graph showing the percentage of queries not answered

C.

PowerPoint presentation outlining the CDI goals and objectives

D.

line graph showing ROM and SOI by month

Question 39

A patient with dysphagia after a recent stroke develops fever, hypoxia, and a right lower-lobe infiltrate. The physician documents “pneumonia.” Speech therapy documents repeated aspiration with oral intake. What is the MOST appropriate CDI action?

Options:

A.

Change pneumonia to aspiration pneumonia

B.

Query the physician regarding the type or etiology of pneumonia

C.

Code aspiration pneumonia from the speech therapist's documentation

D.

Assign both bacterial and aspiration pneumonia

Question 40

A CDI program is developing a query escalation policy. A clinically significant query remains unanswered despite normal reminders. Which action is MOST appropriate?

Options:

A.

Automatically select the diagnosis most strongly supported by CDI

B.

Follow the organization's defined escalation pathway

C.

Remove the query so it cannot delay billing

D.

Ask coding to choose the diagnosis instead of the provider

Question 41

A CDI specialist sends a compliant query. The physician answers “other—viral syndrome” and supports the diagnosis in the progress note. The queried diagnosis would have been an MCC. What should the CDI specialist do?

Options:

A.

Reject the answer because it does not produce an MCC

B.

Accept the clinically supported provider response

C.

Reissue the same query until the provider selects the MCC

D.

Ask coding to assign the MCC anyway

Question 42

A patient is admitted with fever and weakness. On hospital day 3, final blood cultures identify an infection that the physician documents was present at the time of admission. Which statement about present-on-admission status is MOST accurate?

Options:

A.

The diagnosis cannot be POA because it was not identified until hospital day 3

B.

A condition may be POA even when it is diagnosed after admission

C.

All diagnoses first documented after admission receive POA indicator N

D.

Only the principal diagnosis can receive POA indicator Y

Question 43

The progress note on hospital day 2 of a patient's admission states that the patient got up from the bed to go to the bathroom just after housekeeping had mopped the floor. The patient slipped and fell onto the floor, sustaining a broken wrist. The diagnosis of a fractured wrist will:

Options:

A.

Be coded and assigned a POA of “U”

B.

Not be recognized as a CC because it was a hospital-acquired condition

C.

Be considered a CC for calculation of the final MS-DRG

D.

Not be coded because it is a hospital-acquired condition

Question 44

Which of the following programs specifically reduces applicable Medicare payments by 1% for hospitals in the worst-performing quartile based on hospital-acquired-condition measures?

Options:

A.

Hospital Value-Based Purchasing Program

B.

Hospital-Acquired Condition Reduction Program

C.

Medicare Shared Savings Program

D.

Inpatient Psychiatric Facility Quality Reporting Program

Question 45

Documentation indicates an excisional debridement was performed without further specification. The CDI specialist should query to clarify which of the following?

Options:

A.

instrument used in the debridement

B.

depth of debridement

C.

size of debridement

D.

who performed the debridement

Page: 1 / 11
Total 150 questions
