
Which CMS resource contains the complete FY 2026 lists of diagnoses classified as MCCs and CCs for MS-DRG purposes?
The table below shows physician performance:
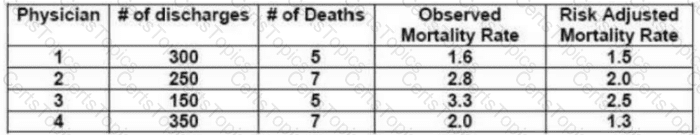
Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?
A patient's baseline creatinine is 1.1 mg/dL. On admission it is 1.2 mg/dL, and 36 hours later it rises to 2.4 mg/dL after prolonged hypotension. Urine output declines substantially. Which condition presents the strongest clarification opportunity?
A CDI program is piloting a new query form to better capture the documentation of pneumonia specificity. Which of the following would be the BEST indicator to determine the effectiveness of the query form?
Copyright © 2021-2026 CertsTopics. All Rights Reserved
